03 / Independent work by Kush Rishi
TrueMargin
Can disagreement between image registrations reveal alignment error?
Experiments on whether variation between image alignments helps identify spatial error. The study compares error estimates with known deformations and simpler methods.
Same anatomy.
Different signals.
Does registration disagreement track alignment error?
Rank correlation with error (Spearman ρ)
0.880spread0.725comparator
30 controlled cases · 10 anatomies. Correlation measures ordering, not error in millimetres. These data do not establish an advantage over inverse-consistency error.
Data and provenance
| Anatomy | Spread | ICE | Residual | Jacobian |
|---|---|---|---|---|
| aaa0044 | 0.8804 | 0.7248 | 0.3013 | 0.6581 |
| aaa0051 | 0.6100 | 0.7158 | 0.5602 | 0.3026 |
| aaa0053 | 0.8902 | 0.9165 | 0.5456 | 0.6571 |
| aaa0060 | 0.2244 | 0.2829 | 0.0912 | 0.0353 |
| aaa0064 | 0.7924 | 0.9064 | 0.7831 | 0.6758 |
| aaa0069 | 0.0334 | -0.0976 | 0.2008 | -0.3014 |
| aaa0071 | 0.7048 | 0.7951 | 0.2843 | 0.8000 |
| aaa0072 | 0.6634 | 0.5898 | 0.2715 | -0.4307 |
| aaa0086 | 0.7763 | 0.7832 | 0.2167 | -0.4467 |
| aaa0087 | 0.3048 | 0.3463 | 0.2860 | -0.3671 |
Display rounding only. Comparator failures and valid-case counts are retained in the source record.
The question
Image registration aligns two scans. This study asks whether variation between registrations identifies local spatial error. Error ranking, blind spots and calibrated bounds are evaluated separately.
Method
A fixed nine-setting ensemble produces displacement fields. Their local spread is compared with known error from synthetic deformations, inverse-consistency error, image residual and Jacobian deviation.
- 01Align images with fixed parameter settings
- 02Measure displacement disagreement
- 03Compare with known error and baselines
The controlled study contains 30 cases across 10 anatomies and 1,500 sampled locations. Anatomy-level summaries avoid counting spatial samples as independent subjects.
Experiments
The first study measured associations and failure cases. A separate calibration study used 30 calibration and 30 evaluation anatomies across two sources. The interactive plot shows retained comparator data, not simulated results.
Results
| Signal | Correlation |
|---|---|
| Ensemble spread | 0.6841 |
| Inverse-consistency error | 0.7203 |
| Image residual | 0.2851 |
| Jacobian deviation | 0.1689 |
All ten anatomy-level spread/error associations were positive. The median correlation confidence interval was [0.3048, 0.8284]. No advantage over inverse-consistency error was established: the paired difference interval crossed zero.
Registration spread and alignment error
Each anatomy has three synthetic deformations with known alignment errors.
Anatomy-level correlation
Each dot shows an anatomy’s median Spearman correlation with known error.
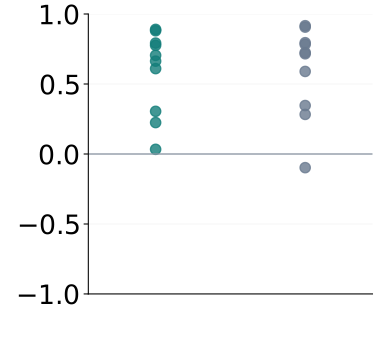
Median 0.6841Inverse-consistency error
Median 0.7203
Spread did not show an advantage over inverse-consistency error. The comparator’s valid-case counts vary by anatomy.
Case-level correlations
Spread/error correlations for all 30 deformation cases.
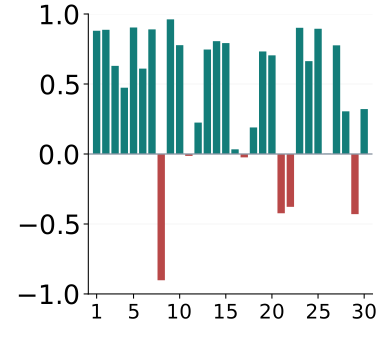
Six correlations were negative.
39 of 1,500 sampled locations had high error despite low spread. Locations are not independent patients.
Exact retained values and sampling units
Ten anatomies × three deformations × 50 locations. The source tables preserve exact values and case ordering.
Anatomy-level results and valid-case counts · Case-level resultsOriginal technical figure. Calibration results below use a separate cohort.
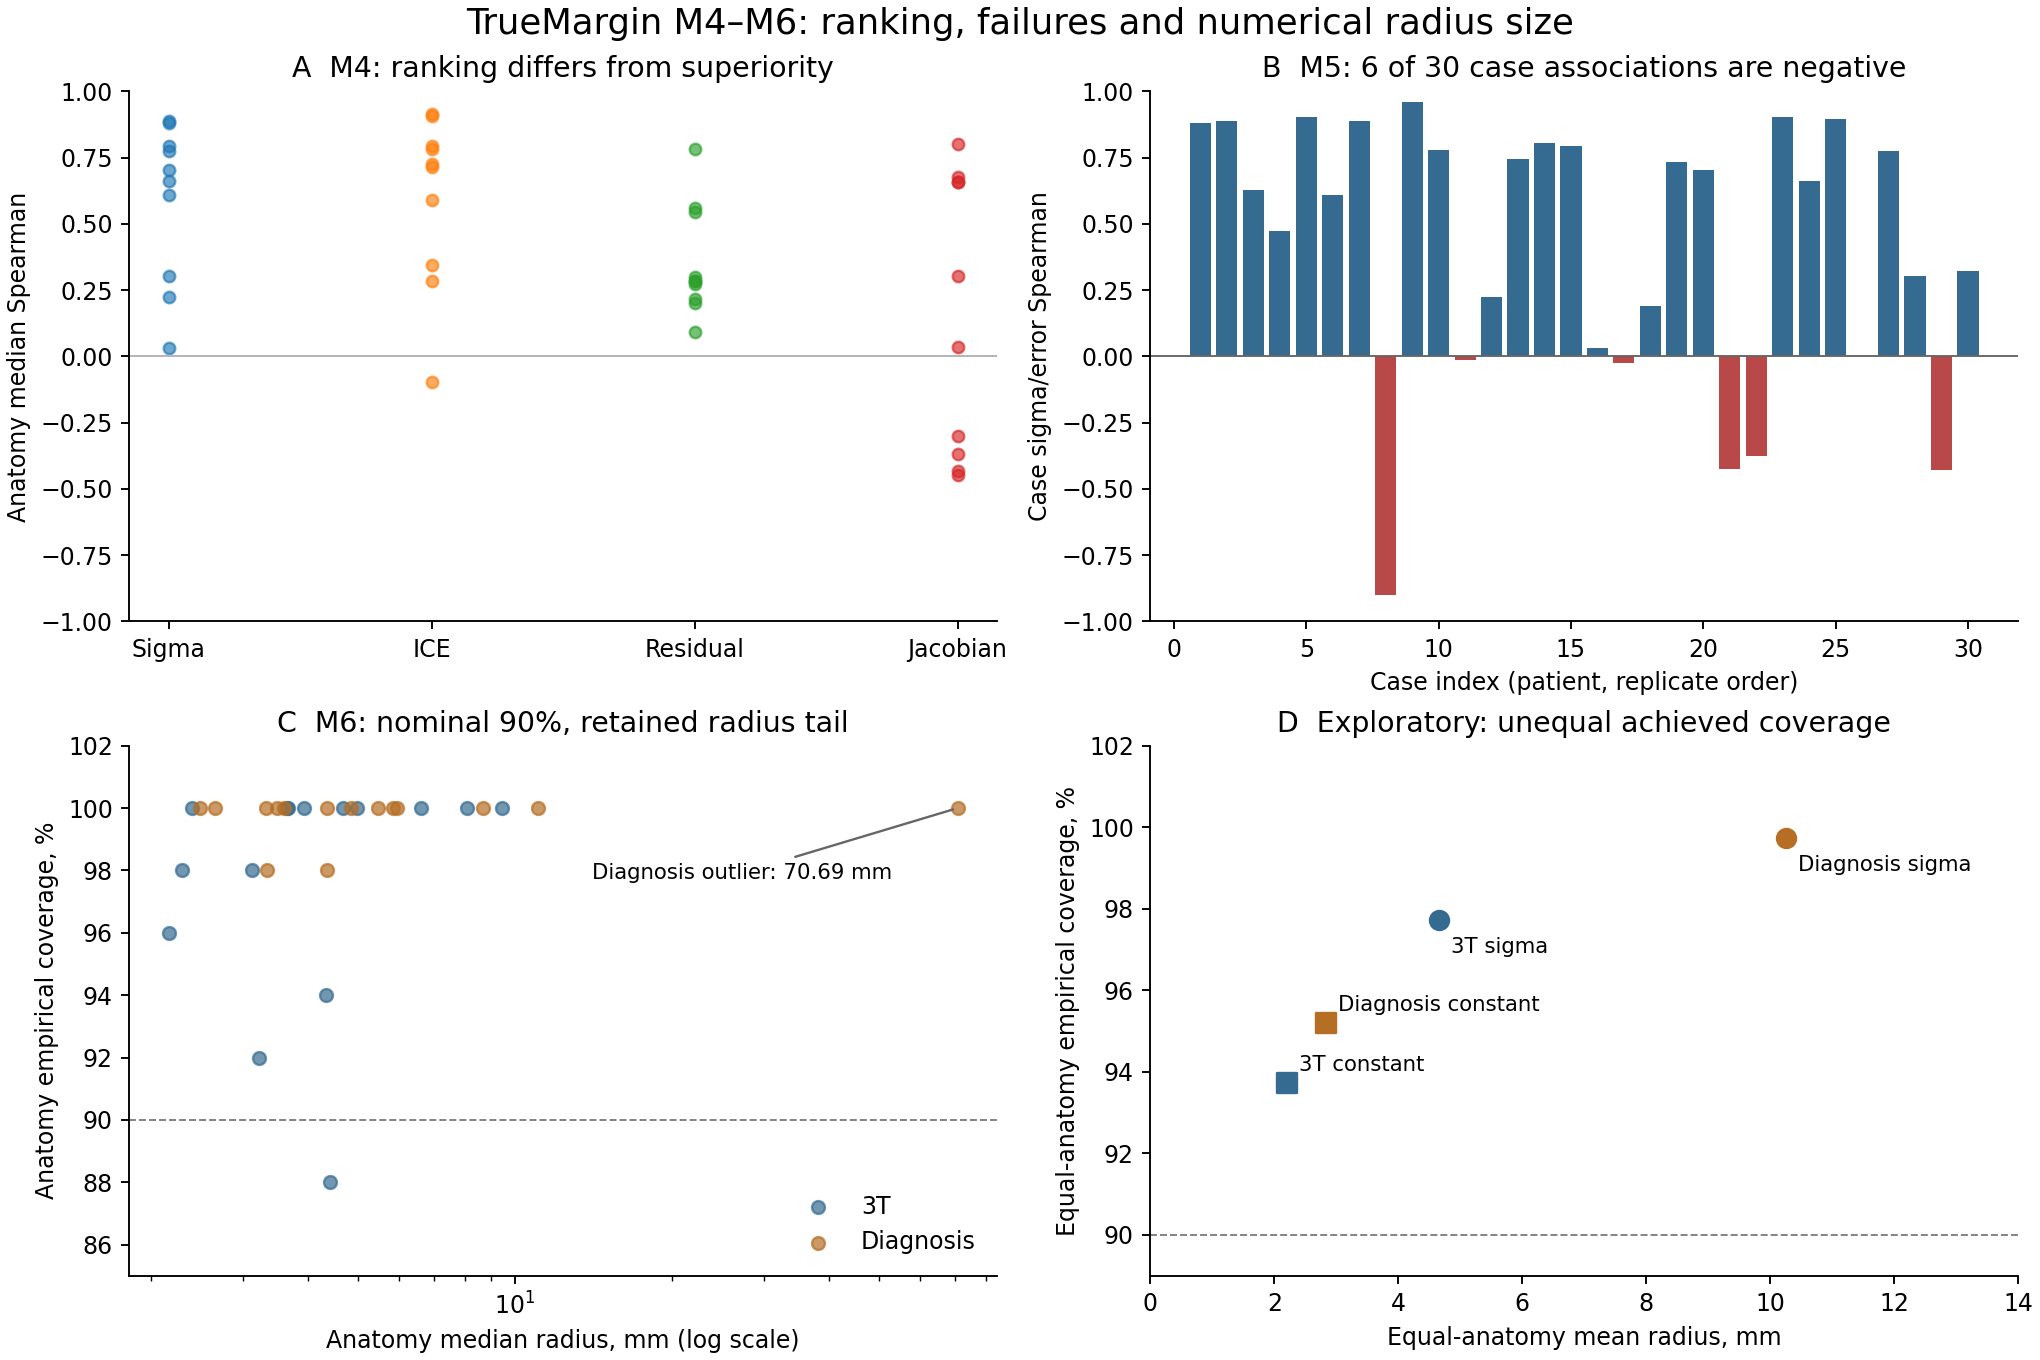
Failures and bounds
Six of 30 case-level correlations were negative. Thirty-nine of 1,500 observations had high error despite low spread; these failures remain in the analysis.
At nominal 90% coverage, the separate evaluation reached 97.73% and 99.73% mean anatomy-level coverage, with median anatomy radii of 3.93 mm and 4.36 mm. One anatomy had a 70.69 mm median radius. The 95% thresholds were infinite with fifteen calibration groups per source. Reverse-registration failures prevented the planned full-cohort calibrated baseline comparison.
Limitations
These studies do not establish clinical validity, external generalization or uniformly useful bounds. A later calibration-only analysis found source-dependent effects, not a consistent improvement. The work has a technical report, not an accepted peer-reviewed publication.
Reproducibility
From a checkout with Python 3.12, check the saved calibration and evaluation records without imaging data:
python scripts/verify_m6_phase_a_result.py results/m6_phase_a
python scripts/verify_m6_phase_b_result.py results/m6_phase_b
These checks do not rerun registrations. Full experiments require the source data and documented imaging dependencies.
Deferred external study
An independent lung-CT protocol and initial image checks were prepared. Two retained Case7 fields were almost identical after a tolerance change; both reached the iteration cap. This establishes neither convergence nor useful ensemble diversity. Numerical landmarks remain sealed and external landmark validation has not run.